Clinical progress has made tumor-directed immunity a major research field. Antigen presentation, T cell specificity and functional persistence remain central questions.
Different treatments engage different parts of immunity
Cancer immunotherapy changes how the immune system recognizes, responds to or controls a tumor. Its success depends on the mechanism being tested and the biological setting in which that mechanism operates.
Checkpoint blockade, cancer vaccines and adoptive T cell therapies have different starting points. A checkpoint inhibitor can release inhibitory signals in an existing immune response. A vaccine supplies antigens intended to elicit or strengthen recognition. Cell therapy supplies selected or engineered effectors. Each approach leaves research questions about specificity, tumor heterogeneity and persistence.
Approach
Biological mechanism
Research question relevant to APC systems
Checkpoint blockade
Modulates inhibitory signaling in immune responses
Are tumor-reactive cells present, and how does the intervention affect priming or effector function?
Antigen-directed vaccination
Introduces antigenic material for immune recognition
Is the intended peptide presented, and does it generate a relevant T cell response?
TIL approaches
Use lymphocytes obtained from tumor tissue
Which expanded cells recognize endogenous tumor antigens?
TCR-directed approaches
Recognize a defined peptide in an appropriate HLA context
Does recognition depend on the intended antigen and HLA, including in tumor cells?
Conventional CAR approaches
Recognize accessible cell surface targets
How do heterogeneous target expression and repeated challenge affect function? CAR recognition can bypass peptide–HLA recognition.
APC systems are especially informative for antigen-specific priming and TCR-mediated recognition. Their relevance to a CAR or other surface-targeted study depends on the question; the distinct recognition mechanisms should be kept explicit. Recent clinical studies provide motivation for this research, while their outcomes should not be transferred to a particular laboratory platform. [1][2][3]
02 / Selected recent advances
Recent clinical advances
The examples below distinguish regulatory milestones, randomized long-term evidence and early-phase studies. They illustrate the field rather than provide a complete treatment survey.
2022Randomized phase 3
TIL therapy versus ipilimumab in advanced melanoma
In a randomized phase 3 trial of 168 patients, 86% of whom had received prior anti-PD-1 therapy, TIL therapy improved median progression-free survival to 7.2 versus 3.1 months with ipilimumab (hazard ratio for progression or death 0.50, 95% CI 0.35–0.72). Objective response was 49% versus 21%. [19]
The trial was open-label and progression-free survival was the primary endpoint. Grade 3 or higher treatment-related adverse events occurred in all patients in the TIL group, whose regimen includes lymphodepletion and IL-2, and in 57% of patients given ipilimumab. The result applies to this melanoma setting.
2024Regulatory milestones
TIL and antigen/HLA-directed T cell approaches
The FDA granted accelerated approval to lifileucel for previously treated advanced melanoma, and to afamitresgene autoleucel for a defined HLA- and MAGE-A4-positive synovial sarcoma population. In the lifileucel label, the single-arm analysis of 73 patients reported an objective response rate of 31.5% (95% CI 21.1–43.4), including complete responses in 4.1%. These milestones emphasize tumor recognition and, for a TCR-directed approach, antigen/HLA selection. [2][3]
Lifileucel received accelerated approval based on response rate, and continued approval may depend on a confirmatory trial. The approved settings are specific. They do not establish activity for other antigens, tumors or research configurations.
2024–25Randomized trial follow-up
Durable outcomes with checkpoint blockade
The final 10-year CheckMate 067 report documents long-term survival in advanced melanoma after nivolumab-containing regimens. It makes durability a measurable outcome while leaving the mechanisms of response and resistance important research questions. [1]
Results come from a specific disease and treatment setting and cannot be generalized to every solid tumor.
2025Phase 1 follow-up
Persistent neoantigen-specific T cells in pancreatic cancer
At extended follow-up, a small individualized RNA vaccine study found sustained functional CD8+ responses in vaccine responders. Immune response correlated with delayed recurrence. [4]
The study combined vaccination with other treatments and was not a randomized demonstration of vaccine efficacy. Immune persistence and clinical benefit require separate evaluation.
2026Phase 1/2 study
Testing multiple antigen targets in pancreatic cancer
A study treated 37 patients with autologous T cells directed at five tumor-associated antigens. Outcomes differed by cohort: arm A reached a 23.1% objective response rate, while the refractory cohort had no objective responses. [5]
The predefined feasibility criterion for completing six infusions was not met in any arm, often because disease progression prevented completion. This supports investigating antigen breadth and persistence while keeping efficacy questions open.
2026Phase 2b follow-up and phase 3 readout
Individualized neoantigen mRNA vaccine with PD-1 blockade
Five-year follow-up of KEYNOTE-942 (phase 2b, 157 patients with resected high-risk melanoma) reported a recurrence-free survival hazard ratio of 0.510 (95% CI 0.294–0.887) for intismeran autogene plus pembrolizumab versus pembrolizumab alone. [10] The phase 3 INTerpath-001 trial (1,137 patients, resected stage IIB–IV melanoma) met its primary recurrence-free survival endpoint and the key secondary distant metastasis-free survival endpoint. [11]
The phase 2b result is from an open-label study of 157 patients, and the phase 3 hazard ratios have not yet been released. Both are melanoma studies in the adjuvant setting and do not transfer to other tumors or antigens.
2026Regulatory milestone
First approval of a solid tumor CAR-T product
China’s NMPA approved satricabtagene autoleucel, a claudin18.2-directed CAR-T, for CLDN18.2-positive, HER2-negative advanced gastric or gastroesophageal junction adenocarcinoma after at least two prior lines of therapy. Median progression-free survival was 3.25 versus 1.77 months with physician’s choice (HR 0.37). [17]
Grade 3 or higher adverse events occurred in 99% of the 88 evaluable patients, and the pivotal study was phase 1b/2. The approval shows that surface target selection remains the central variable for solid tumor cell therapy.
Research context reviewed October 4, 2026. A publication date and study type accompany each example.
03 / Field trends
Field trends
Across modalities, the recent record shares one feature: benefit depends on choosing a target that is recognized and tumor-specific. The table lists the evidence behind each trend and what it implies for antigen discovery. Trials differ in design and disease, so the rows are not head-to-head comparisons.
Trend
Evidence
Implication for antigen discovery
HLA-restricted TCR-based biologics
Tebentafusp in HLA-A*02:01-positive metastatic uveal melanoma (378 patients): 5-year overall survival 16% versus 8%, HR 0.67 (95% CI 0.54–0.85). [16]
Recognition of a peptide–HLA target can deliver survival benefit, so peptide identity and HLA context must be defined.
T cell engagers for surface antigens
Tarlatamab (DLL3 × CD3) in relapsed small-cell lung cancer, DeLLphi-304 (phase 3, 509 patients): median overall survival 13.6 versus 8.3 months, HR 0.60. [15]
Surface antigen engagers succeed when the target is expressed and tumor-selective; target nomination remains the first step.
APC-based cell therapy
Sipuleucel-T, an autologous product of blood mononuclear cells that include antigen-presenting cells, activated with PAP-GM-CSF, in castration-resistant prostate cancer (IMPACT, 512 patients): median overall survival 25.8 versus 21.7 months, HR 0.78. [14][24]
An APC-containing cellular product improved survival in one setting, which established antigen presentation as a therapeutic principle.
Dendritic cell function
Dendritic cells take up tumor antigen and prime T cells, and their function depends on activation state and context. [13]
APC models should report phenotype and be tested for antigen presentation rather than assumed to present.
Antigen selection
TESLA consortium: 37 of 608 tested neoantigen candidates (6%) were recognized by T cells. Binding affinity, tumor abundance and binding stability together improved prediction. [12]
Prediction ranks candidates; a functional presentation and recognition assay decides.
Regulatory direction
On April 10, 2025, the FDA announced a plan to reduce animal testing requirements for monoclonal antibodies and other drugs, naming new approach methodologies that include computational models, cell lines and organoids. [18]
Human cell-based assays are gaining weight in preclinical packages. This is general direction, not guidance specific to APC-based assays.
Source types (journal article, regulatory announcement, company press release, conference report) are identified in each reference entry.
04 / Unmet research needs
Responses can fail at several steps
A response can fail before priming, during recognition or after repeated exposure to the tumor. Laboratory studies become more informative when they isolate the step being tested rather than treat every reduction in killing as the same problem.
Biological barrier
Why it matters
An interpretable research question
Antigen heterogeneity and escape
Target expression can differ among cells and change under immune pressure.
Does a response control mixed antigen-positive and antigen-negative targets?
Antigen processing and HLA presentation
An expressed protein may not yield the peptide–HLA target recognized by a T cell.
Can the intended peptide be detected, and do functional controls support HLA-dependent recognition?
Inadequate priming or response breadth
General activation or cell expansion can occur without the desired specificity.
Which antigen-specific responses arise, and how broad are they?
Inhibitory or inflammatory context
Cell contact signals and soluble factors can change APC, effector and target cell behavior.
Which component changes, and is the effect independent of toxicity?
Loss of function with repeated challenge
Acute cytolysis does not establish recall, persistence or sustained control.
How do response magnitude and function change after serial antigen or target exposure?
Donor and model context
HLA, effector cell source, culture state and target processing influence interpretation.
Does a finding reproduce across the contexts relevant to the research claim?
Patient studies show that failures in antigen presentation or interferon-response pathways can accompany acquired resistance. A KRAS-directed T cell case also illustrates escape associated with loss of the restricting HLA allele. These observations justify testing presentation and recognition directly. [6][7]
The same logic applies upstream. When 25 groups ranked neoantigen candidates and 608 were tested, 37 (6%) were recognized by T cells, so a predicted epitope is a hypothesis until a T cell assay supports it. [12]
The fraction recognized depends on what is counted. TESLA counted peptides that prediction pipelines had already prioritized. In a screen of mutated gene products from patients with gastrointestinal cancers, 1.6% were recognized by autologous TIL, yet neoantigen-reactive TIL were found in 62 of 75 patients (83%). [20] Neither figure predicts the yield of a particular discovery pipeline, so report the denominator with any immunogenicity rate.
Cell-based assays can investigate these mechanisms, but a coculture does not reproduce all features of a solid tumor. Questions about trafficking, stromal barriers and the tissue microenvironment may require complementary models.
05 / The DC–antigen–T cell relationship
Presentation connects an antigen to an immune response
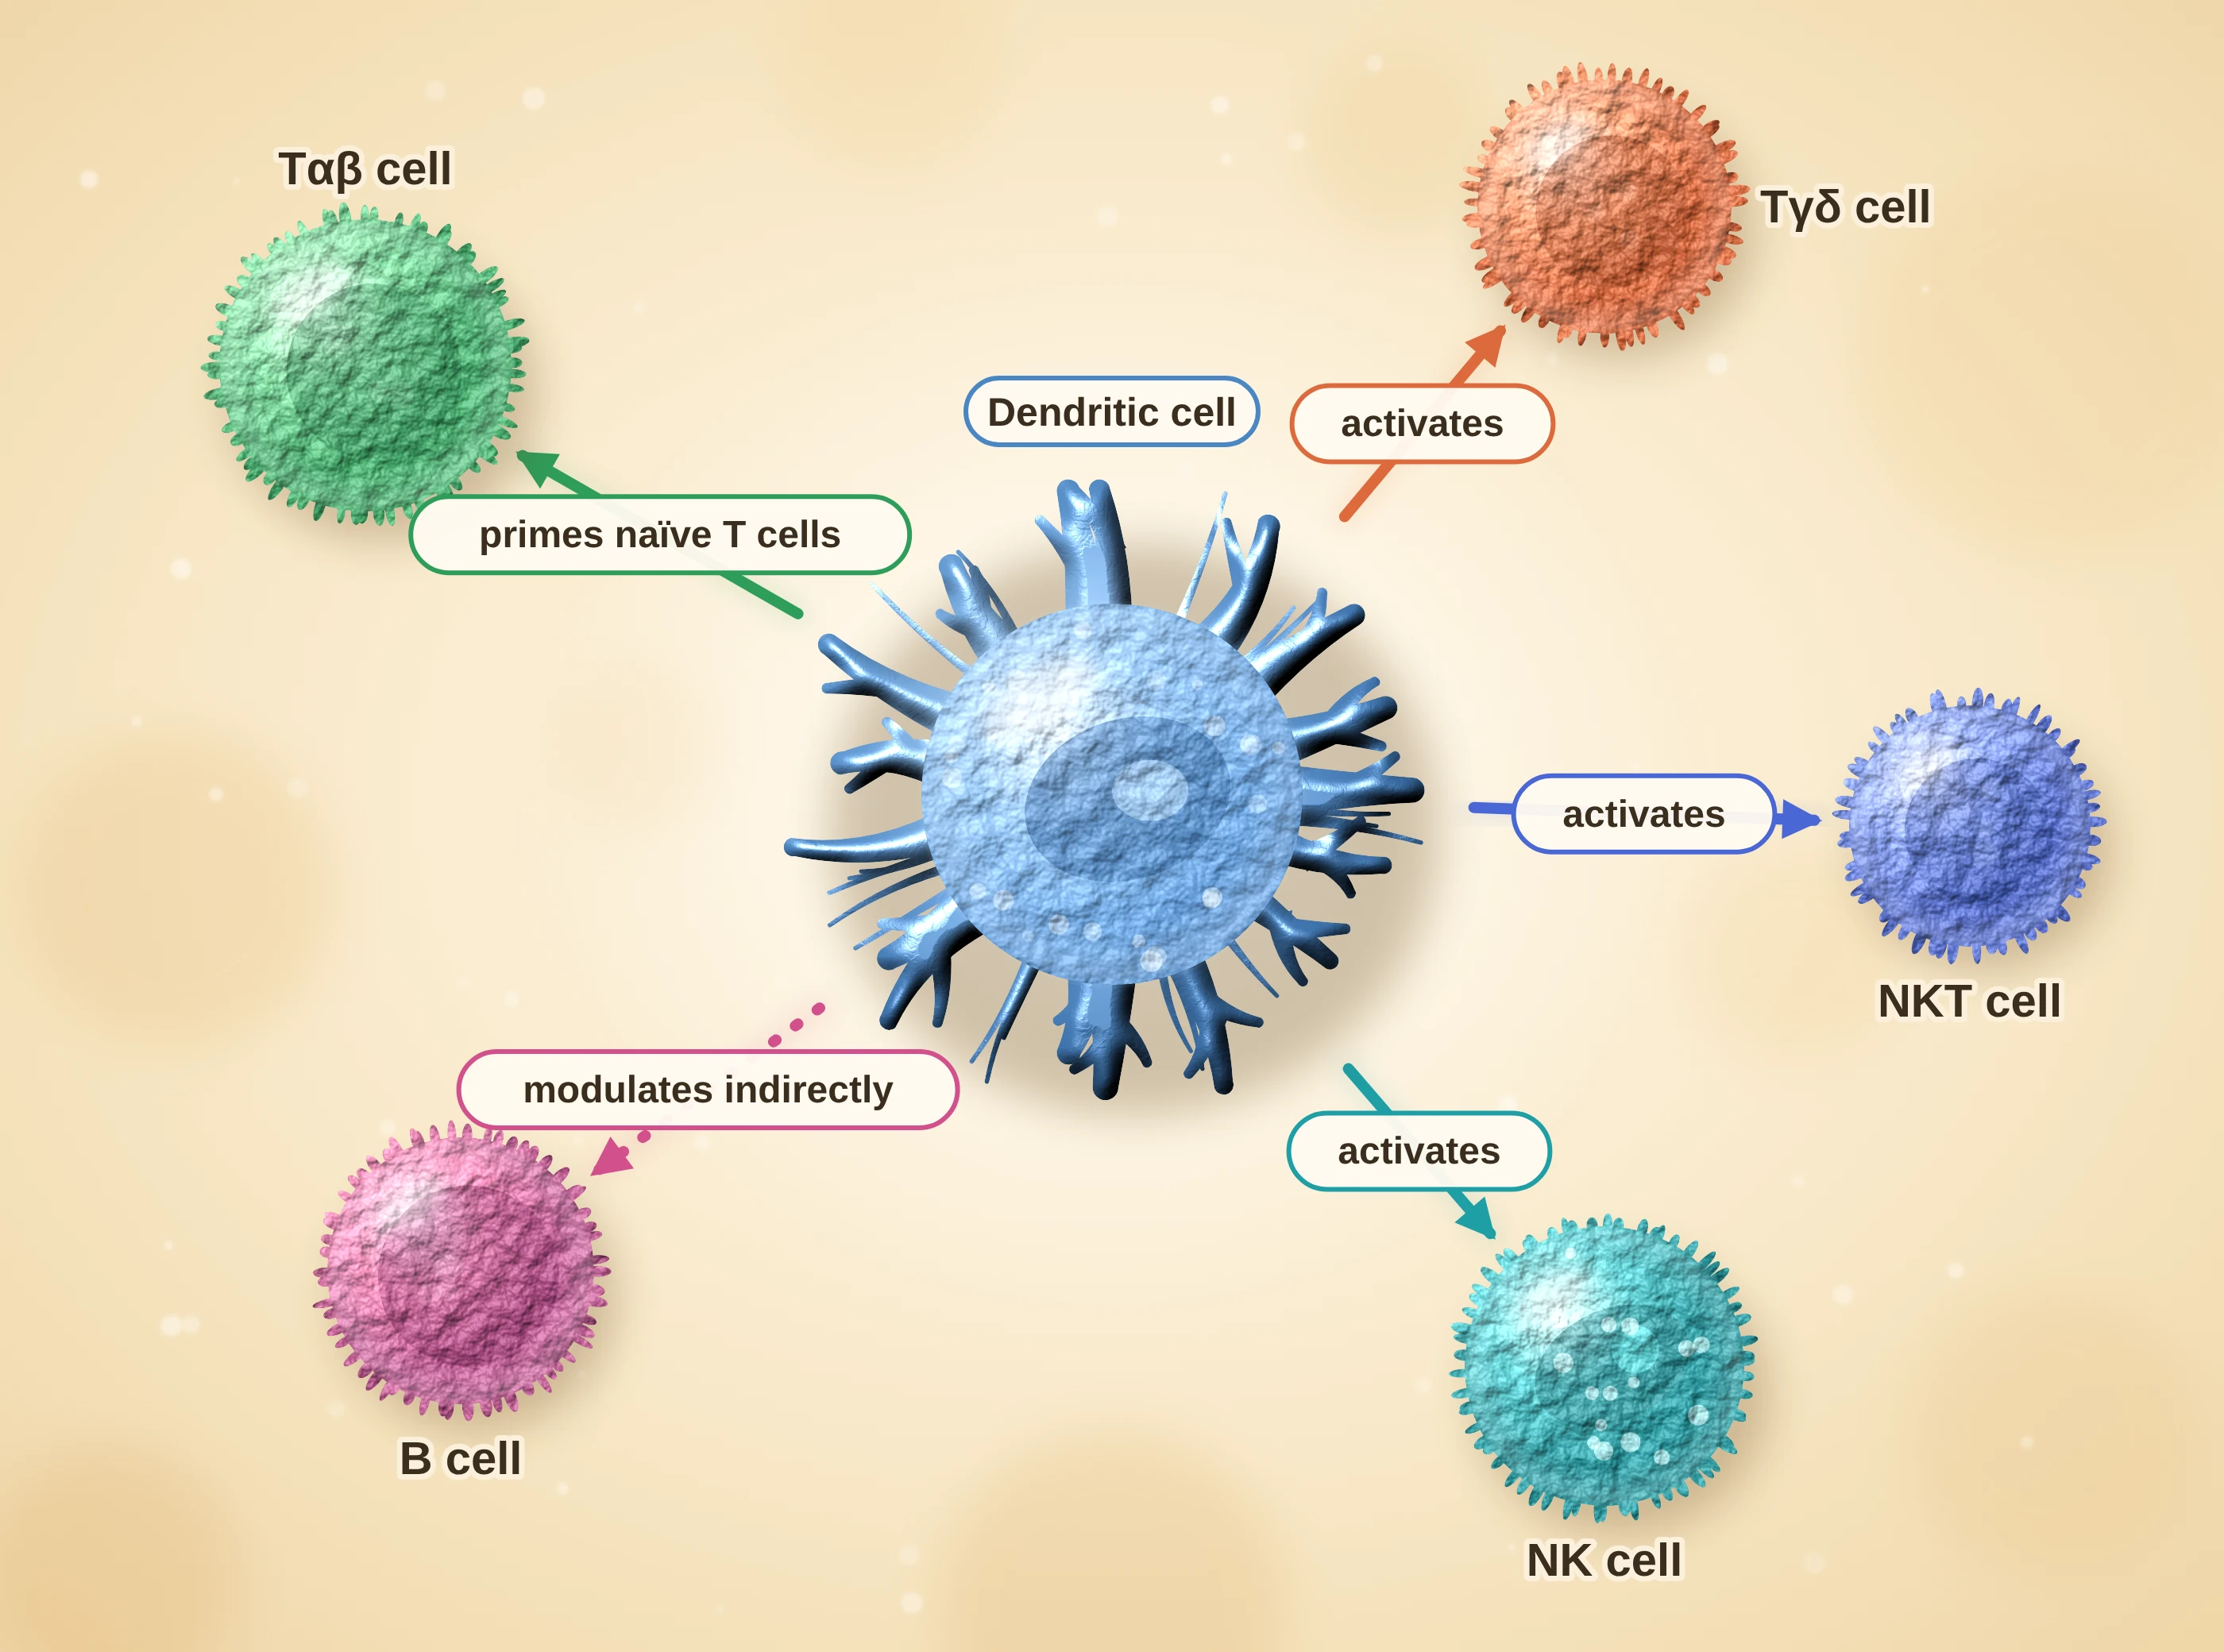
Dendritic cells are professional antigen-presenting cells. Their value in research comes from bringing antigen presentation together with signals that shape T cell priming. Human DC studies demonstrate both antigen presentation capability and the importance of culture and maturation conditions. [8][9]
A dendritic cell model is best described by its activation state and its measured capacity to present antigen to T cells. Antigen uptake and processing, HLA presentation, costimulation and the cytokine context together determine whether a T cell response is primed, so each should be tested in the experimental system rather than assumed. [13]
Tαβ cells
DCs prime naïve Tαβ cells to differentiate into tumor- or virus-antigen-specific cytotoxic effector T cells.
Tγδ cells
DCs can activate Tγδ cells, which have broad anti-cancer activity. γδ T cell insight ›
NK and NKT cells
DCs can activate NK and NKT cells and promote their proliferation through soluble factors and surface activating molecules. DC–NK insight ›
B cells
DCs modulate B cell function indirectly, including antibody production.
Dendritic cells connect antigen presentation with several effector arms. Original conceptual illustration, not experimental data.
01
Antigen source
A tumor-associated protein, mutation-derived antigen or defined fragment supplies the material being investigated.
02
Processing & presentation
Peptides associate with HLA molecules. Class I presentation informs CD8+ recognition, while class II presentation informs CD4+ recognition.
03
Recognition & priming
The TCR engages a peptide–HLA target. Costimulation and the cytokine context shape the resulting response.
04
Functional assessment
Test the effector response against relevant targets, with antigen, HLA and background controls.
Conceptual biological sequence. The steps describe separate experimental questions, not a validated performance specification.
The antigen, HLA and T cell receptor must be considered together
For a conventional antigen-specific T cell response, the recognized target is a peptide–HLA complex. Antigen expression alone does not establish that a particular peptide is processed, presented at sufficient abundance or recognized. A peptide-loaded APC, an APC expressing an antigen fragment and a tumor expressing an endogenous protein may also process antigen differently.
Priming depends on more than receptor engagement
Costimulatory interactions, including the CD80/CD86–CD28 pathway, and local cytokine signals contribute to T cell activation and differentiation. CD4+ help can also shape responses. A marker panel is useful characterization, but its presence does not establish the specificity or function of the responding cells.
APC-derived signals also act on NK cells
NK cell activation and expansion depend on cytokine and costimulatory signals that antigen-presenting cells and feeder cells can supply. Activated monocytes present IL-15 in trans on IL-15Rα, so a responding cell that expresses only IL-2/15Rβ and the common γ chain still receives the signal. [21] K562 feeder cells engineered to express membrane-bound IL-15 and 4-1BBL expanded human NK cells by a median of 21.6-fold at 7 days (range 5.1–86.6; n = 50). [22] Brief pre-activation with IL-12, IL-15 and IL-18 produces cytokine-induced memory-like NK cells. In a phase 1 study of nine evaluable patients with acute myeloid leukemia, five had clinical responses, four of them complete remissions. [23]
These studies used monocytes, K562 feeder cells and recombinant cytokines. They identify signals worth measuring and do not describe eDC performance. Whether a given APC line supplies IL-15 presentation or 4-1BBL, and whether that changes NK activation, proliferation or target cell killing, is an experimental question. 4-1BBL is among the markers on the eDC phenotype panel, with a modest shift. A matched coculture, with and without APC gene knockout and a separated cell control, can test the contribution. DC–NK study design ›
Why this relationship matters for discovery
A defined APC system lets researchers perturb antigen configuration or an APC gene, then ask whether the effect reaches the T cell response. Paired target cells extend the question to function. This connects a candidate mechanism to measurable biology, with controls that help distinguish APC effects from effector toxicity or changes in target susceptibility.
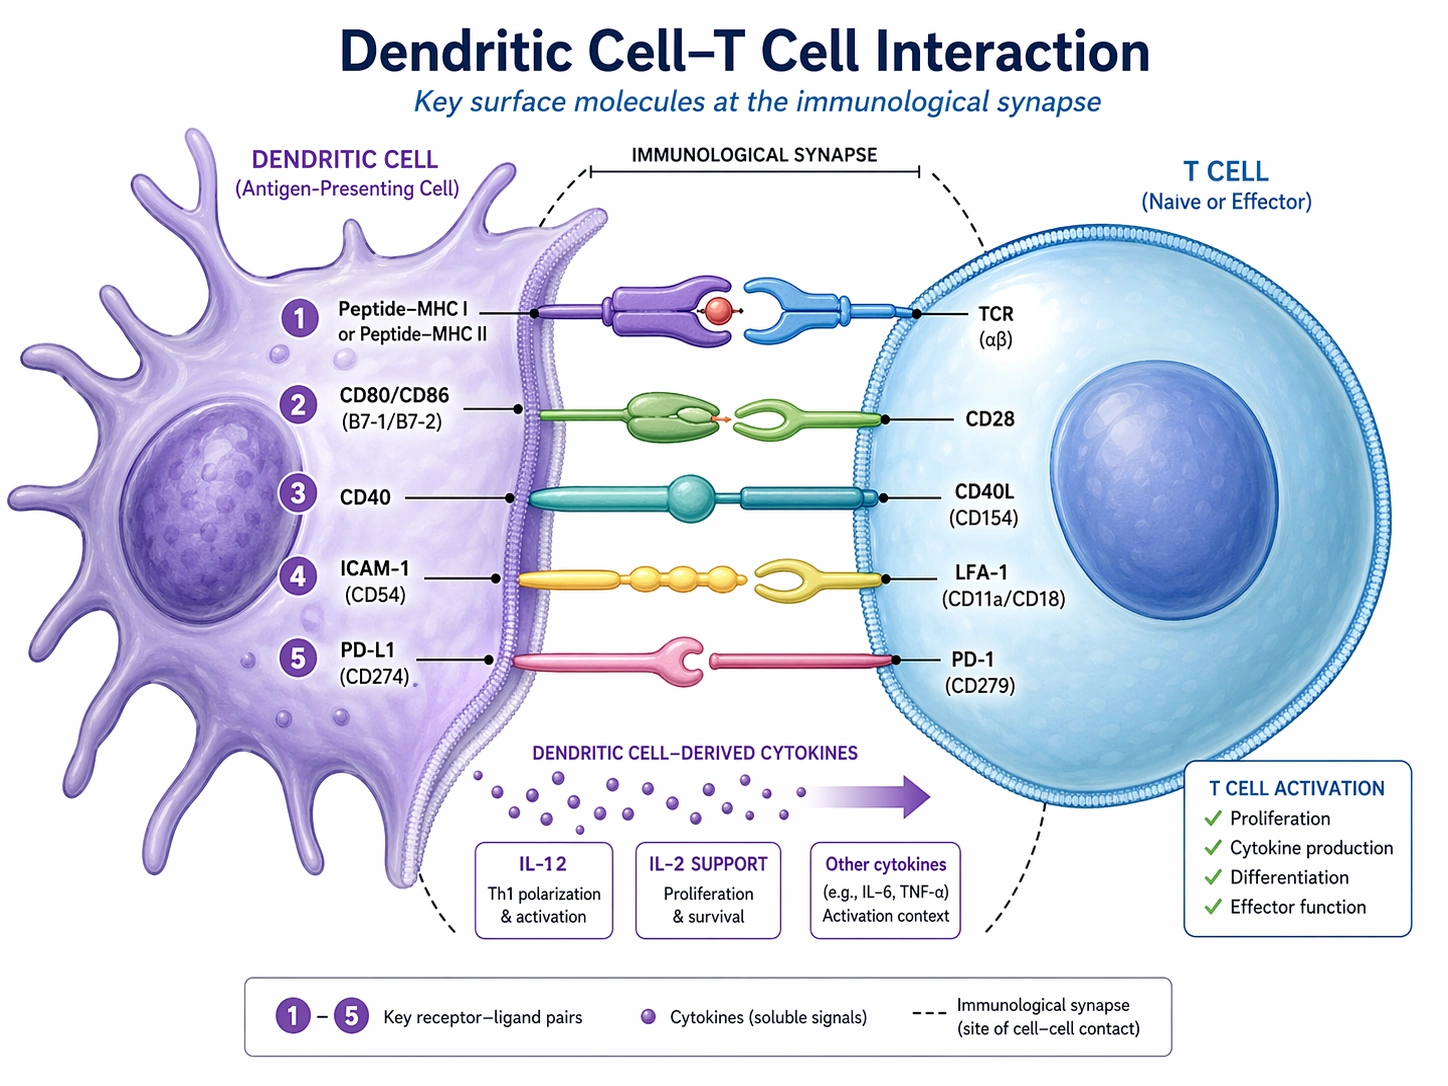
Molecular interactions that shape a T cell response. Conceptual overview of activating, adhesive and inhibitory interactions. Molecule expression and cytokine sources depend on cell state and culture conditions.
Read the molecular interface
Five interactions, different biological roles
01
Peptide–HLA ↔ TCR: antigen recognition
The receptor recognizes a particular peptide in a compatible HLA context. Class I–restricted recognition involves CD8 T cells; class II–restricted recognition involves CD4 T cells. The diagram shows alternatives, rather than one TCR recognizing both classes.
02
CD80/CD86 ↔ CD28: costimulation
Costimulation helps shape activation alongside antigen recognition. A functional study should account for the APC state and the responder population, rather than infer activity from antigen expression alone.
03
CD40 ↔ CD40L: helper cell feedback
Activated CD4 helper T cells can provide CD40L signals to DCs, influencing their ability to support a response, including IL-12 production in appropriate contexts. This interaction is not a universal feature of every naïve T cell. Primary study ›
04
ICAM-1 ↔ LFA-1: cell contact
Adhesion helps organize and maintain cell–cell contact. Contact duration, antigen dose and the state of both cells can affect the response measured in an assay.
05
PD-L1 ↔ PD-1: inhibitory regulation
This axis can attenuate T cell signaling. Its role is distinct from the activating interactions in the diagram, and provides a mechanism to investigate in checkpoint-related experiments. Primary study ›
Read cytokines in their experimental context
IL-12 can support type 1 responses. IL-2 supports T cell proliferation and survival, but should not be described as a uniform secretion feature of all DC preparations. Activated T cells and, under particular conditions, DCs can contribute to IL-2 biology. Measure the relevant source, concentration and timing in the study. Human DC–T cell study ›
The illustration explains general immunology; it does not define the molecular profile of every eDC configuration.
Short science explainer
DC–T cell interaction
DC–T cell interaction: recognition, signaling and function. 100-second conceptual animation with narration and on-screen explanations. Receptor engagement, intracellular signals and cytokine movement are illustrated; this is not live-cell microscopy.Read the narration transcript
Dendritic cells connect antigen detection with T cell responses. At their contact site, called the immunological synapse, several molecular interactions work together.
A peptide displayed by an HLA molecule engages a compatible T cell receptor. Class I presentation is recognized by CD8 T cells. Class II presentation is recognized by CD4 T cells.
Recognition alone does not explain the full response. CD80 and CD86 can engage CD28, while adhesion molecules help maintain contact. Signals then travel into the T cell.
Activated helper T cells can provide CD40 ligand to dendritic cells. Cytokines shape the response. IL-12 can favor type 1 immunity. IL-2 supports T cell growth, with its source depending on the experimental context.
Inhibitory interactions also matter. PD-L1 binding PD-1 can reduce T cell signaling. Activation reflects the balance of antigen recognition, costimulation, cytokines and inhibitory signals.
For drug discovery, measure more than cell numbers. Test antigen and HLA dependence, cytokine responses, and activity against paired target cells. These complementary readouts connect the mechanism to the biological question.
Mechanism of action
Dendritic cell licensing and CD8 T cell priming
Dendritic cell licensing and CD8 T cell priming. Conceptual animation of about three minutes, with narration and on-screen labels. It follows an immature dendritic cell through innate maturation, CD4 T cell help and licensing to CD8 T cell priming. Receptor engagement and cytokine release are illustrated; this is not live-cell microscopy and it does not define the molecular profile of any specific eDC configuration.Stages shown in the animation
Stage 0, immature dendritic cell. Basal co-stimulation, with low CD40 on the cell surface.
Stage 1, innate maturation (TLR signal). CD40 and CD80/CD86 are upregulated and IL-12p40 is primed.
CD4 T cell handshake. A TLR-matured dendritic cell presents antigen on MHC class II with CD80/CD86 to a naive CD4 helper T cell. Activation leads to CD40 ligand and IFN-γ.
Stage 2, adaptive licensing (CD40 and IFN-γ). CD80/CD86 reach peak density, CD70 is high, IL-12p70 is released in a burst and Bcl-xL supports survival.
Licensed cDC1 output and CD8 priming. CD70 engaging CD27, together with IL-12p70, supports clonal expansion of CD8 cytotoxic T cells, shown delivering cytotoxic granules to a tumor cell.
Explore the biology
Research insights
Each insight connects a mechanism to an experimental question, with an original diagram.
The platform assists scientists and biotech laboratories with research findings and drug target discovery. A useful experiment defines which component the intervention is expected to affect and measures the others as possible confounders: antigen recognition, APC gene function, compound effects, response breadth and persistence, and antigen/HLA dependence.
Candidate peptides, tetramer binding and cytokine release are useful parts of an evidence package and answer different questions. Recognition of a relevant target expressing the endogenous antigen is particularly valuable when the claim concerns tumor cell recognition.
KRAS: an intracellular target makes presentation central
Mutant KRAS illustrates why the compartment containing an antigen matters. A conventional CAR recognizing a surface protein does not directly recognize intracellular KRAS. A TCR-mediated response can recognize a KRAS-derived peptide in a suitable HLA context, if processing, presentation and specificity are demonstrated.
In a published colorectal cancer case, seven lesions regressed after transfer of KRAS G12D-reactive T cells; one later progressed with loss of the restricting HLA-C*08:02 allele. This is evidence in a particular patient and HLA setting, not proof for every KRAS variant or HLA allele. [6]
Antigen breadth and repeated APC support raise testable laboratory questions: does the intended antigen reach peptide–HLA presentation, do effectors recognize endogenous targets, and is function retained under repeated or heterogeneous challenge?
A renewable, antigen-defined cellular starting point
CrossRelay focuses on antigen-expressing eDC lines, paired target cell assay systems and supporting culture cytokines. Custom development begins with customer-provided PBMCs and may include agreed genetic modifications, such as a gene knockout.
The scientific value is the ability to work with a selected antigen/HLA configuration across related experiments. A renewable line still requires characterization of identity, antigen expression, culture behavior and functional performance in the relevant passage window. It represents a defined model rather than the full diversity of donors or tissue DC states.
MD54.1 expresses an hTERT fragment (aa 301–700) covering known HLA-A2.1- and HLA-A*24:02-restricted epitopes. Fragment coverage is a configuration description; epitope-specific processing and presentation must be established separately. The proposed growth factor cocktail and final specifications for each line remain in development.
Phenotype, morphology and the comparison with the conventional MoDC method are documented on the eDC technology page.
Original functional data
Original research figures illustrate functional assessment in defined antigen and HLA settings. Each result should be interpreted within its tested configuration. Full figures, experimental context and downloads are on the product pages.
hTERT
Antigen dependence and HLA restriction
eDC-stimulated cytotoxic T lymphocytes were tested against U2OS-Luc and U2OS-Luc/TERT targets, with HLA-A2.1 blockade. Higher cytolysis of the TERT-positive model and reduced cytolysis under blockade are consistent with antigen-related, HLA-dependent activity.
The same effector system was tested against A549 and H1299 lung cancer target models with different antigen and HLA-A2.1 configurations. Activity varies with target configuration and E:T ratio.
Flow cytometry panels, cytokine readouts and A549 cytolysis describe different parts of the response. A population phenotype alone does not establish antigen specificity.
Replicate counts, gating details and definitions of statistical symbols are stated with each figure where available. These findings apply to the illustrated experiments and are not release specifications.
Wolchok JD et al. Final, 10-Year Outcomes with Nivolumab plus Ipilimumab in Advanced Melanoma. N Engl J Med. 2025;392:11–22. Published online September 15, 2024. DOI: 10.1056/NEJMoa2407417. Read source ›
FDA. Afamitresgene autoleucel: accelerated approval for selected HLA- and MAGE-A4-positive synovial sarcoma, August 2, 2024. Read source ›
Sethna Z et al. RNA neoantigen vaccines prime long-lived CD8+ T cells in pancreatic cancer. Nature. 2025;639:1042–1051. DOI: 10.1038/s41586-024-08508-4. Read source ›
Musher BL et al. Autologous multiantigen-targeted T cell therapy for pancreatic cancer: a phase 1/2 trial. Nature Medicine. 2026;32:258–269. DOI: 10.1038/s41591-025-04043-5. Read source ›
Tran E et al. T Cell Transfer Therapy Targeting Mutant KRAS in Cancer. N Engl J Med. 2016;375:2255–2262. DOI: 10.1056/NEJMoa1609279. Read source ›
Zaretsky JM et al. Mutations Associated with Acquired Resistance to PD-1 Blockade in Melanoma. N Engl J Med. 2016;375:819–829. DOI: 10.1056/NEJMoa1604958. Read source ›
Sallusto F, Lanzavecchia A. Efficient presentation of soluble antigen by cultured human dendritic cells. J Exp Med. 1994;179:1109–1118. DOI: 10.1084/jem.179.4.1109. Read source ›
Ferlazzo G et al. Dendritic cells generated either from CD34+ progenitor cells or from monocytes differ in their ability to activate antigen-specific CD8+ T cells. J Immunol. 1999;163:3597–3604. Read source ›
Moderna and Merck. Five-year data for intismeran autogene in combination with pembrolizumab in resected high-risk melanoma (KEYNOTE-942, phase 2b); company press release, January 20, 2026. Read source ›
Merck and Moderna. INTerpath-001 phase 3 topline results, August 2026, as reported by The ASCO Post. Full data to be presented at a future meeting. Read source ›
Wells DK et al. Key parameters of tumor epitope immunogenicity revealed through a consortium approach improve neoantigen prediction. Cell. 2020;183:818–834. DOI: 10.1016/j.cell.2020.09.015. Read source ›
Murphy TL, Murphy KM. Dendritic cells in cancer immunology. Cell Mol Immunol. 2022;19:3–13. DOI: 10.1038/s41423-021-00741-5. Read source ›
Kantoff PW et al. Sipuleucel-T immunotherapy for castration-resistant prostate cancer. N Engl J Med. 2010;363:411–422. DOI: 10.1056/NEJMoa1001294. Read source ›
Amgen. Tarlatamab (IMDELLTRA) DeLLphi-304 phase 3 results, press release, June 2025; published in N Engl J Med, 2025. Read source ›
Five-year survival with tebentafusp in HLA-A*02:01-positive metastatic uveal melanoma (IMCgp100-202), presented at the AACR Annual Meeting, April 2026; OncLive report, April 21, 2026. Read source ›
OncLive. China’s NMPA approves first CAR T cell therapy for CLDN18.2-positive, HER2-negative advanced gastric/GEJ adenocarcinoma (satricabtagene autoleucel), June 22, 2026. Read source ›
FDA. FDA announces plan to phase out animal testing requirement for monoclonal antibodies and other drugs, April 10, 2025. Read source ›
Rohaan MW et al. Tumor-infiltrating lymphocyte therapy or ipilimumab in advanced melanoma. N Engl J Med. 2022;387:2113–2125. DOI: 10.1056/NEJMoa2210233. Read source ›
Parkhurst MR et al. Unique neoantigens arise from somatic mutations in patients with gastrointestinal cancers. Cancer Discov. 2019;9:1022–1035. DOI: 10.1158/2159-8290.CD-18-1494. Read source ›
Dubois S, Mariner J, Waldmann TA, Tagaya Y. IL-15Rα recycles and presents IL-15 in trans to neighboring cells. Immunity. 2002;17:537–547. Read source ›
Fujisaki H et al. Expansion of highly cytotoxic human natural killer cells for cancer cell therapy. Cancer Res. 2009;69:4010–4017. DOI: 10.1158/0008-5472.CAN-08-3712. Read source ›
Romee R et al. Cytokine-induced memory-like natural killer cells exhibit enhanced responses against myeloid leukemia. Sci Transl Med. 2016;8:357ra123. DOI: 10.1126/scitranslmed.aaf2341. Read source ›
Clinical studies inform the research questions discussed here. For an eDC study, evaluate the antigen configuration, HLA context and functional evidence documented for the selected line.
Selected publications
PNAS · 2018
Induction of antitumor cytotoxic lymphocytes using engineered human primary blood dendritic cells
Wu L, Zhang H, Jiang Y, Gallo RC, Cheng H. 115(19):E4453–E4462. DOI: 10.1073/pnas.1800550115.